 How-to
Common Blood Tests for Autoimmune Disease Diagnosis
Last Updated: November 7, 2026
Quick Summary
Common blood tests for autoimmune disease diagnosis include ANA, ESR and CRP, CBC with differential, CMP, rheumatoid factor, and urinalysis, with disease-specific antibodies added when screening points somewhere. No single test confirms or rules out an autoimmune disease, so results only mean something when read alongside your symptoms, medical history, and a physical exam.
- A positive ANA is common in healthy people, so it works as a screening test rather than a diagnostic one.
- ESR and CRP show that inflammation is present but cannot reveal which condition is causing it.
- Many panels such as a CMP ask for an 8- to 12-hour fast, while a stand-alone ANA usually does not.
- Screening tests like CBC, CMP, ESR, or CRP often return within a few days, while specialized antibody tests can take longer.
- A normal result does not rule out autoimmune disease, especially early on or between flares.
Table of Contents
- Why Autoimmune Blood Tests Rarely Stand Alone
- The Autoimmune Blood Test Panel List: What Each Test Detects
- Inflammation Markers: ESR, CRP, and What They Signal
- Complete Blood Count, Metabolic Panel, and Organ Function
- When an Autoimmune Blood Test Is Positive
- What an Autoimmune Blood Test Normal Range Really Means
- A Test-Selection Map by Symptom and Suspected Condition
- Preparation, Sample Collection, and Turnaround Times
- What to Do After Your Results Come Back
- Applying for a Root-Cause Review of Your Labs
- Frequently Asked Questions
Why Autoimmune Blood Tests Rarely Stand Alone
Common blood tests for autoimmune disease diagnosis are tools for gathering clues, not verdicts. No single blood test confirms or rules out an autoimmune disease on its own. A result only means something when it is read alongside your symptoms, your medical history, and a physical examination. Patients often arrive with a stack of labs marked "normal" and still feel unwell.
That is the core tension in autoimmune testing. Labs measure markers. They do not measure how you feel, how you sleep, or how your body is functioning day to day.
Here is what most guides get wrong: they present each test as a yes-or-no answer. In practice, each test is a piece of a puzzle.
- A positive result can appear in people with no disease at all.
- A negative result can appear in people who clearly have one.
- Timing matters, because antibody levels can rise and fall.
This is why a practical guide to tracking symptoms before a diagnosis matters so much. Symptoms give the labs their context.
What is an autoimmune disease?
An autoimmune disease is a condition in which the immune system mistakenly attacks the body's own healthy cells and tissues. Examples include lupus, rheumatoid arthritis, and autoimmune thyroid disease. Blood tests look for the antibodies and inflammation patterns these conditions tend to produce.
The Autoimmune Blood Test Panel List: What Each Test Detects
An autoimmune blood test panel list usually starts with a few broad screening tests, then narrows toward disease-specific antibodies. Your doctor picks the starting point based on your symptoms, not a standard one-size-fits-all order.
The first-line tests typically include:
- ANA (antinuclear antibody): a broad screening test for autoimmune activity
- ESR and CRP: markers of inflammation
- CBC with differential: a look at your blood cell counts
- CMP: a check on organ function, including liver and kidneys
- Rheumatoid factor (RF): often ordered when joints are involved
- Urinalysis: checks kidney health, which matters in conditions like lupus
If a screening test points somewhere, your doctor may add disease-specific antibodies. To see how functional medicine testing for autoimmune thyroid expands on standard panels, that comparison is worth a look. That is how a broad panel becomes a targeted one.
Antinuclear Antibody (ANA) and Staining Patterns
The ANA test is the most common screening test for autoimmune disease. It looks for antibodies that target the nucleus of your own cells. A lab usually runs it with an indirect immunofluorescence assay (IFA), which shows both an ANA titer and a staining pattern.
The ANA titer tells you how dilute the sample can be before the signal disappears. The staining pattern hints at which antibodies may be present. A high titer with a specific pattern points your doctor in one direction. A low titer with a nonspecific pattern points nowhere in particular.
Here is the part people miss: a positive ANA is common in healthy people too. It is a screening test, not a diagnostic test. The result only carries weight when it fits your symptoms.
Rheumatoid Factor and Disease-Specific Antibodies
Rheumatoid factor (RF) is an antibody often found in rheumatoid arthritis, but it can show up in other rheumatic disease and in some healthy people. So RF alone cannot confirm rheumatoid arthritis.
Disease-specific antibodies are more targeted. These include:
- Anti-dsDNA: strongly tied to lupus
- Anti-CCP: more specific for rheumatoid arthritis
- Extractable nuclear antigens (ENA): a group of antibodies linked to lupus and other connective tissue diseases
- Thyroid antibodies: linked to autoimmune thyroid disease
Each has different sensitivity and specificity. That means each one is better at ruling a condition in than ruling it out.
Inflammation Markers: ESR, CRP, and What They Signal
Inflammation markers show that your immune system is active, but not why. Two of the most common are the erythrocyte sedimentation rate (ESR) and C-reactive protein (CRP).
ESR measures how fast red blood cells settle in a tube. A faster rate can suggest inflammation somewhere in the body. CRP measures a protein the liver makes when inflammation is present.
Both are useful signals, and both are nonspecific. A raised ESR or CRP can come from an infection, an injury, or an autoimmune flare. A normal result does not rule out autoimmune disease either, especially between flares.
Think of these markers as a smoke alarm. They tell you something may be smoldering. They do not tell you which room.
Complete Blood Count, Metabolic Panel, and Organ Function
A complete blood count (CBC) and a comprehensive metabolic panel (CMP) rarely diagnose autoimmune disease directly. What they do is reveal how well your body is functioning, which helps your doctor see the bigger picture.
A CBC with differential counts your red cells, white cells, and platelets. Low counts in certain cell lines can appear in some autoimmune conditions, such as lupus.
A CMP checks organ function, including your liver and kidneys. This matters because some autoimmune diseases, lupus in particular, can affect the kidneys. A urinalysis often joins the CMP for the same reason.
Ferritin, a marker of iron stores, is sometimes added too. It can rise with inflammation, so it adds another clue. None of these tests confirm a diagnosis alone. Together, they show whether your organs are under strain.
When an Autoimmune Blood Test Is Positive
An autoimmune blood test positive result does not mean you have an autoimmune disease. It means your immune system has left a marker that your doctor needs to interpret.
A positive ANA, for example, is common (Antinuclear antibodies in healthy people and non-rheumatic diseases - diagnostic and...). Many people with a positive ANA never develop an autoimmune disorder. The result becomes meaningful when it lines up with symptoms like joint pain, rashes, fatigue, or organ involvement.
Your doctor will typically respond to a positive result by:
- Reviewing your symptoms and medical history in detail
- Ordering more specific antibody tests
- Repeating the test if the result is unclear
- Referring you to a rheumatologist or other specialist
A positive result is a starting point for a conversation, not a diagnosis. That distinction matters, and it is one reason we encourage patients to ask what a result means for them specifically.
What an Autoimmune Blood Test Normal Range Really Means
An autoimmune blood test normal range is a reference range, not a guarantee of health. Labs set these ranges by measuring results in a large group of people and marking the middle spread as "normal."
Two things trip people up here.
First, a result inside the range can still come with symptoms. You can have a normal ANA titer and still have an autoimmune condition, especially early on or between flares. Second, a result just outside the range is not automatically alarming. Reference ranges are statistical, not personal.
This is why reading your results in context matters so much. A number on a page means little without your symptoms, your history, and your doctor's judgment. If you want a walkthrough of how to actually read blood test results, that skill is worth building.
Watch out: do not treat an at-home test result as a diagnosis. A single out-of-range value can trigger unnecessary worry, and a normal value can create false reassurance. Always have a clinician interpret it.
A Test-Selection Map by Symptom and Suspected Condition
Doctors choose tests based on your symptoms. There is no single panel that covers everything, so the starting point shifts with the picture you present. Here is a simplified map of how symptoms tend to guide test selection.
| Symptoms or Suspected Condition | Tests Often Ordered First | What They Look For |
|---|---|---|
| Joint pain, stiffness, swelling | RF, anti-CCP, ESR, CRP | Rheumatoid arthritis and inflammation |
| Fatigue, rash, sun sensitivity | ANA, anti-dsDNA, CBC, urinalysis | Lupus and organ involvement |
| Dry eyes, dry mouth | ANA, ENA panel | Sjögren's and connective tissue disease |
| Fatigue, weight change, hair loss | Thyroid antibodies, TSH | Autoimmune thyroid disease |
| Unexplained inflammation | ESR, CRP, CBC, CMP | General inflammation and organ function |
This map is a starting point, not a prescription. Your doctor adjusts it based on your history and exam findings. The right panel for you depends on your whole picture.
Preparation, Sample Collection, and Turnaround Times
Most autoimmune blood tests need little preparation, but a few practical details make the draw smoother and the results more reliable. Knowing what to expect also reduces the chance that a preventable issue forces a repeat visit.
Before the appointment
- Fasting: Many panels, including a comprehensive metabolic panel (CMP) and a lipid panel, ask for an 8- to 12-hour fast. A stand-alone ANA, ESR, or CRP usually does not require fasting. Follow the specific instructions your ordering clinician or lab gives you, because the requirements differ by test.
- Medications: Tell your clinician about everything you take, including over-the-counter drugs and supplements. Some medications can influence inflammation markers or antibody levels, and your clinician may time a test around a medication rather than stop it on your own.
- Timing: Some antibody tests are most informative when symptoms are active. If you are tracking flares, note the date and severity so your clinician can compare the result to your clinical picture.
- Hydration: Drinking water before a draw makes veins easier to find and can reduce the number of needle sticks.
- Recent illness: A recent infection, injury, or vaccination can temporarily raise inflammation markers. Mention any recent illness so the result is read in context.
What happens during collection
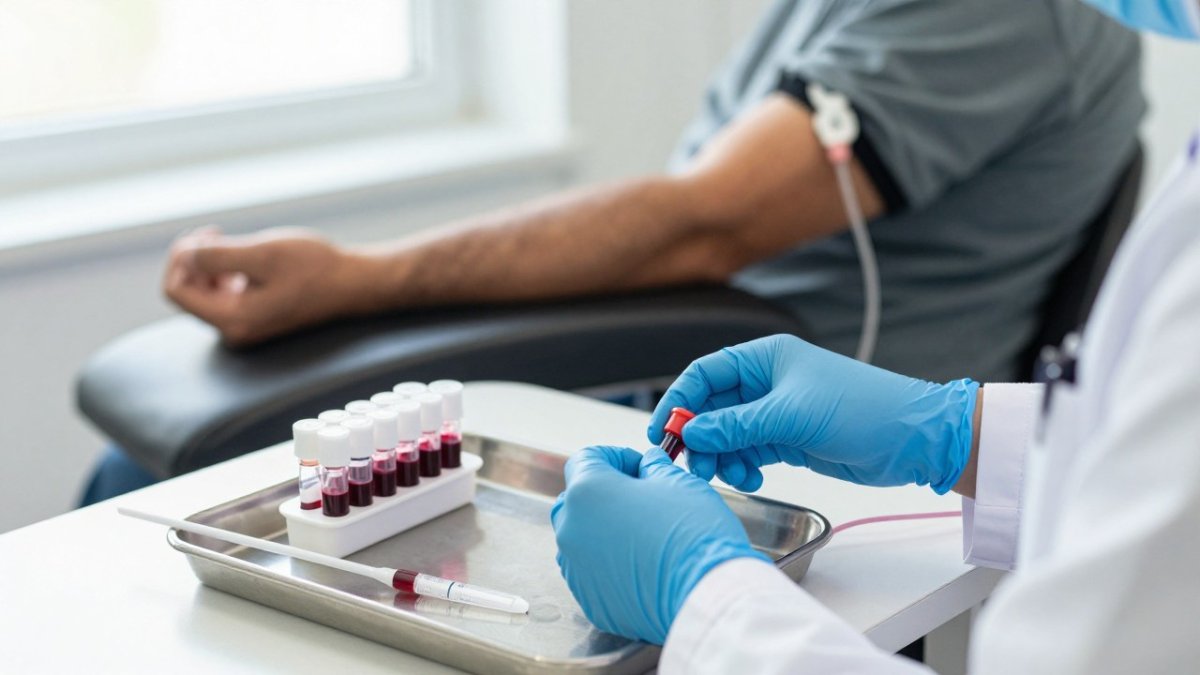
A standard blood draw takes only a few minutes. A phlebotomist cleans the site, applies a tourniquet, inserts a needle into a vein (usually in the arm), and collects one or more tubes. Different tests require different tube types, which is why you may see several tubes filled in sequence. After the draw, the site is bandaged and you can usually drive yourself home.
Watch out: Do not stop a prescribed medication before testing without talking to your clinician first; some drugs need to be tapered rather than stopped abruptly.
Turnaround times
Turnaround varies by test and by lab. Common screening tests such as a CBC, CMP, ESR, or CRP often return within a few days. Specialized antibody tests, including some ENA panels and anti-dsDNA, can take longer because they may be sent to a reference laboratory. Ask the lab or your clinician's office what to expect for each test so you are not left guessing, and ask how results will be communicated to you.
Repeat testing
Your clinician may repeat a test rather than act on a single value. Antibody levels can rise and fall over time, and a result that was borderline or unclear may become clearer on a repeat draw weeks later. If you are tracking a known condition, keep a simple log of dates, results, and symptoms so trends are visible rather than isolated numbers.
What to Do After Your Results Come Back
Once results are in, the next step is interpretation with a qualified professional, not a search engine. The right response depends on whether your results are abnormal, normal, or inconclusive, and on how they line up with your symptoms.
If a result is abnormal
An abnormal result is a signal to investigate, not a diagnosis. Your clinician will typically review your symptoms and history, consider whether the value fits a pattern, and decide whether more specific antibody tests are warranted. Ask which values are outside the reference range, by how much, and whether the pattern points toward a particular condition. A referral to a rheumatologist or other specialist is common when results suggest a connective tissue disease or when the picture is complex.
If a result is normal
A normal result does not rule out autoimmune disease, especially early in a condition or between flares. If your symptoms persist, tell your clinician. They may repeat testing later, order different tests, or look for non-autoimmune explanations. A normal value should not create false reassurance when symptoms are ongoing.
If a result is inconclusive or borderline
Borderline results are common with screening tests such as ANA. Your clinician may repeat the test, add a more specific antibody test, or simply monitor over time. Ask what would change the interpretation and when a repeat draw makes sense.
Questions worth asking your clinician
- Which results are outside the reference range, and by how much?
- Do these results fit my symptoms and history?
- Do I need repeat or follow-up testing, and when?
- Should I see a specialist, and which one?
- Could any medication or recent illness have affected these results?
Preparing for a specialist visit
If you are referred, organize your results and symptoms beforehand. A guide on how to prepare for an autoimmune specialist appointment can help you walk in ready. A clear summary of when symptoms started, how they have changed, and which tests were done makes the appointment far more productive. Bring a list of medications and any prior labs so the specialist sees the full picture rather than a single value.
Watch out: Do not treat an at-home or direct-to-consumer test result as a diagnosis. A single out-of-range value can trigger unnecessary worry, and a normal value can create false reassurance. Have a clinician interpret it in context.
If your results are positive or unclear, do not panic and do not self-diagnose. The right move is a calm, structured conversation with a clinician who can connect the dots between your labs, your symptoms, and your history.
Applying for a Root-Cause Review of Your Labs
Standard labs often stop at "normal" or "abnormal." A root-cause review asks a different question: what is driving these results in the first place?
This is where Thyroid Authority fits. Thyroid Authority offers a physician-led, 12-month virtual program designed to help individuals uncover the root causes of their thyroid and autoimmune symptoms. The program uses the proprietary EPIC Five™ Framework to look beyond symptom management.
If you are ready to have your labs reviewed with a root-cause focus, you can book a Complimentary Discovery Session and take the first step.
Autoimmune testing can feel like a maze of numbers and ranges. The path forward is a structured review with a clinician who connects your labs to your symptoms and your history. Thyroid Authority offers physician-led care, a 12-month guided program, and the EPIC Five™ Framework to help you find the root cause and restore your energy. Get started with Thyroid Authority and take back control of your health.
Frequently Asked Questions
Can one blood test diagnose an autoimmune disease?
No. Autoimmune blood tests are pieces of a larger picture, not a verdict on their own. A positive ANA, for example, appears in people without any autoimmune disorder, and a normal result does not rule one out. Doctors combine test results with your symptoms, medical history, physical examination, and sometimes repeat testing over time. That is why a single panel ordered without context can mislead as easily as it informs.
Can autoimmune blood tests be normal even if you have symptoms?
Yes, and this is common. Some people with autoimmune conditions have normal inflammatory markers or negative antibodies early in the disease, or their condition does not produce the specific antibody being tested. A normal range on a lab report means your value falls inside the reference interval for that test, not that your immune system is quiet. If symptoms persist despite normal results, ask for a review of the full pattern rather than accepting the report at face value.
What does a positive ANA blood test mean?
A positive ANA means your immune system produced antibodies that bind to parts of your own cells. It does not mean you have lupus or another autoimmune disorder. Low titers are frequently seen in healthy people, and the staining pattern plus your symptoms matter more than the positive label alone. Doctors typically follow a positive ANA with more specific tests such as anti-dsDNA or extractable nuclear antigens before drawing conclusions.
How do doctors choose which autoimmune blood tests to order?
The choice starts with your symptoms and physical examination. Joint pain and morning stiffness point toward rheumatoid factor and anti-CCP; persistent fatigue with skin or kidney symptoms may prompt ANA and anti-dsDNA; general inflammation gets screened with ESR and CRP. A complete blood count and comprehensive metabolic panel usually come first to check for anemia and organ function. The autoimmune blood test panel list should follow the clinical picture, not run as a fixed bundle for everyone.



